You've been staring at the same jeans for months, and the last diet lasted about three weeks. You want a medical plan, not another reminder to drink more water. Getting treatment isn't one prescription. It's eligibility, a slow dose climb, months of tracking, and a bill you can still pay next winter.
How to get GLP-1 weight loss starts with a clinician, not a coupon. Weekly injections such as semaglutide and tirzepatide, or a daily oral semaglutide pill, only help if you qualify and you can stay on them. "Weekly injection" describes the injectable forms. The pill is a different routine.
Check Whether You Qualify for GLP-1 Treatment
GLP-1 medicines such as semaglutide and tirzepatide are prescription treatments that act on appetite and fullness signals. They work best alongside nutrition and activity, not instead of them.
The threshold you can check in two minutes is a BMI of 30 or higher, or a BMI of 27 or higher with a qualifying condition such as high blood pressure, prediabetes, high cholesterol, or sleep apnea. Below 27, the weight-loss pathway usually isn't open.
| Your situation | Typical outcome | What to bring |
|---|---|---|
| BMI 30 or higher | Usually eligible | Recent weight, height and medical history |
| BMI below 27 | Usually not eligible for weight-loss treatment | Ask whether a different approach fits better |
| Type 2 diabetes | Separate pathway with diabetes-labeled products | A1c results and current diabetes medications |
| Pregnant, planning pregnancy or breastfeeding | Generally not a candidate | Tell the provider before any appointment |
| Personal or family history of medullary thyroid cancer or MEN 2 | Contraindicated | Family medical history |
| Personal history of pancreatitis | Needs provider review before any decision | Prior hospital or lab records |
Diabetes uses its own labeled products, so don't assume a weight-loss brand is the right one. Pregnancy, a pregnancy plan, or breastfeeding takes this option off the table. A personal or family history of medullary thyroid cancer or MEN 2 is a hard stop. Prior pancreatitis isn't an automatic yes or no. It needs records.
The first review is a detailed questionnaire covering BMI, pre-existing conditions, current medications, prior GLP-1 history, and contraindications. A licensed clinician decides eligibility from that history. You don't self-clear.
Before you open the form, pull together height, current weight, recent blood pressure readings, your medication list, and any earlier GLP-1 prescriptions. Missing those details is what stalls people.
Steps to Get a GLP-1 Prescription
Most delays happen before the visit, not during it. Incomplete answers send the chart back. Rushing the pharmacy choice sends the bill back.

Before the visit
-
Confirm BMI and finish the questionnaire. Cover conditions, medications, prior GLP-1 use, and contraindications. A blank field is the slip that causes most delays. Our 2-minute quiz is only a first screen, not a prescription.
-
Book a video visit with a licensed clinician. Eligibility comes from your history and the provider's assessment, not from a score on a website. If the form already points away from treatment, or you have pancreatitis, a pregnancy plan, or a thyroid-cancer history, talk with your primary care clinician about other options first.
What gets decided on the call
-
Choose the form with the clinician, not from an ad. Weekly semaglutide or tirzepatide injections, or a daily oral semaglutide pill, are the usual options. The provider weighs your preferences, medical history, and lifestyle. Daily dosing needs more consistent adherence than one injection a week.
-
Expect baseline checks. Current weight, blood pressure, pregnancy status, gastrointestinal and pancreatitis history, and your current medicines should be on the table. Skipping the stomach history is how people start a dose they can't tolerate.
-
Ask whether the product is an FDA-approved brand or a compounded medication from a U.S. 503A pharmacy. Compounded medication isn't FDA-approved, so ask how it's sourced and monitored. Get the total monthly price in writing before you pick a pharmacy. Our compounded treatment starts at $199 per month, and that figure is a comparison point, not your personal total until it's written down.
After you have a prescription
- Pick one fixed weekly dosing day and book the first follow-up. People quit early when they have no plan for nausea. Don't wait for the second bad week to ask what to do.
Before you accept: If you can't name the product, the monthly total, and what happens when you feel sick, you don't have a plan yet.
Ask these six questions before you say yes:
- Exact product and sourcing: Brand or compounded, and which pharmacy dispenses it.
- Total monthly cost: What the price includes, and what it doesn't.
- Dose schedule: The starting dose and when it can rise.
- Nausea or vomiting: Hold, treat, or call, and who answers.
- A missed dose: The rule for your product, not a guess.
- The six-month plan: Who reviews progress if the scale slows.
Complete the questionnaire today and book the visit only if the answers still fit. A not-yet is a useful result.
How Dose Escalation Works Week by Week
Don't start at the maintenance dose. The FDA prescribing information for Wegovy uses a gradual weekly climb so gastrointestinal effects are less likely to knock you off treatment.
| Weeks on treatment | Weekly dose | What to check before the next step |
|---|---|---|
| Weeks 1 to 4 | 0.25 mg | Nausea, vomiting and fluid intake |
| Weeks 5 to 8 | 0.5 mg | Whether side effects have settled |
| Weeks 9 to 12 | 1 mg | Nutrition, constipation and dehydration |
| Weeks 13 to 16 | 1.7 mg | Weight trend and any missed doses |
| Week 17 onward | 1.7 mg or 2.4 mg | Provider decides between maintenance and 2.4 mg |
The same label allows a four-week delay when a dose isn't tolerated. That's the designed pause, not a failure. Gastrointestinal trouble shows up most often while the dose is rising. Treating the schedule like a race is how people stop early.
Tirzepatide follows a different ladder. It commonly starts at 2.5 mg for four weeks, then moves to 5 mg, with later increases in 2.5 mg steps no sooner than every four weeks. For the oral semaglutide pill, the provider manages the high-dose escalation so side effects stay manageable while you reach an appropriate dose.
Before each step, check nausea, vomiting, constipation, dehydration, and whether you can keep food and fluids down. One weekly dose, same day. Don't speed the titration, and don't double up after a missed dose unless the prescriber says so.
If a step isn't tolerated, ask whether to hold the dose. Don't ask whether to skip ahead.
The label also flags pancreatitis and thyroid C-cell tumors. Ongoing symptom review isn't optional paperwork. Judge the scale over months, along with waist, blood pressure, nutrition, activity, and muscle, not after week two.
What Progress to Expect and How to Track It
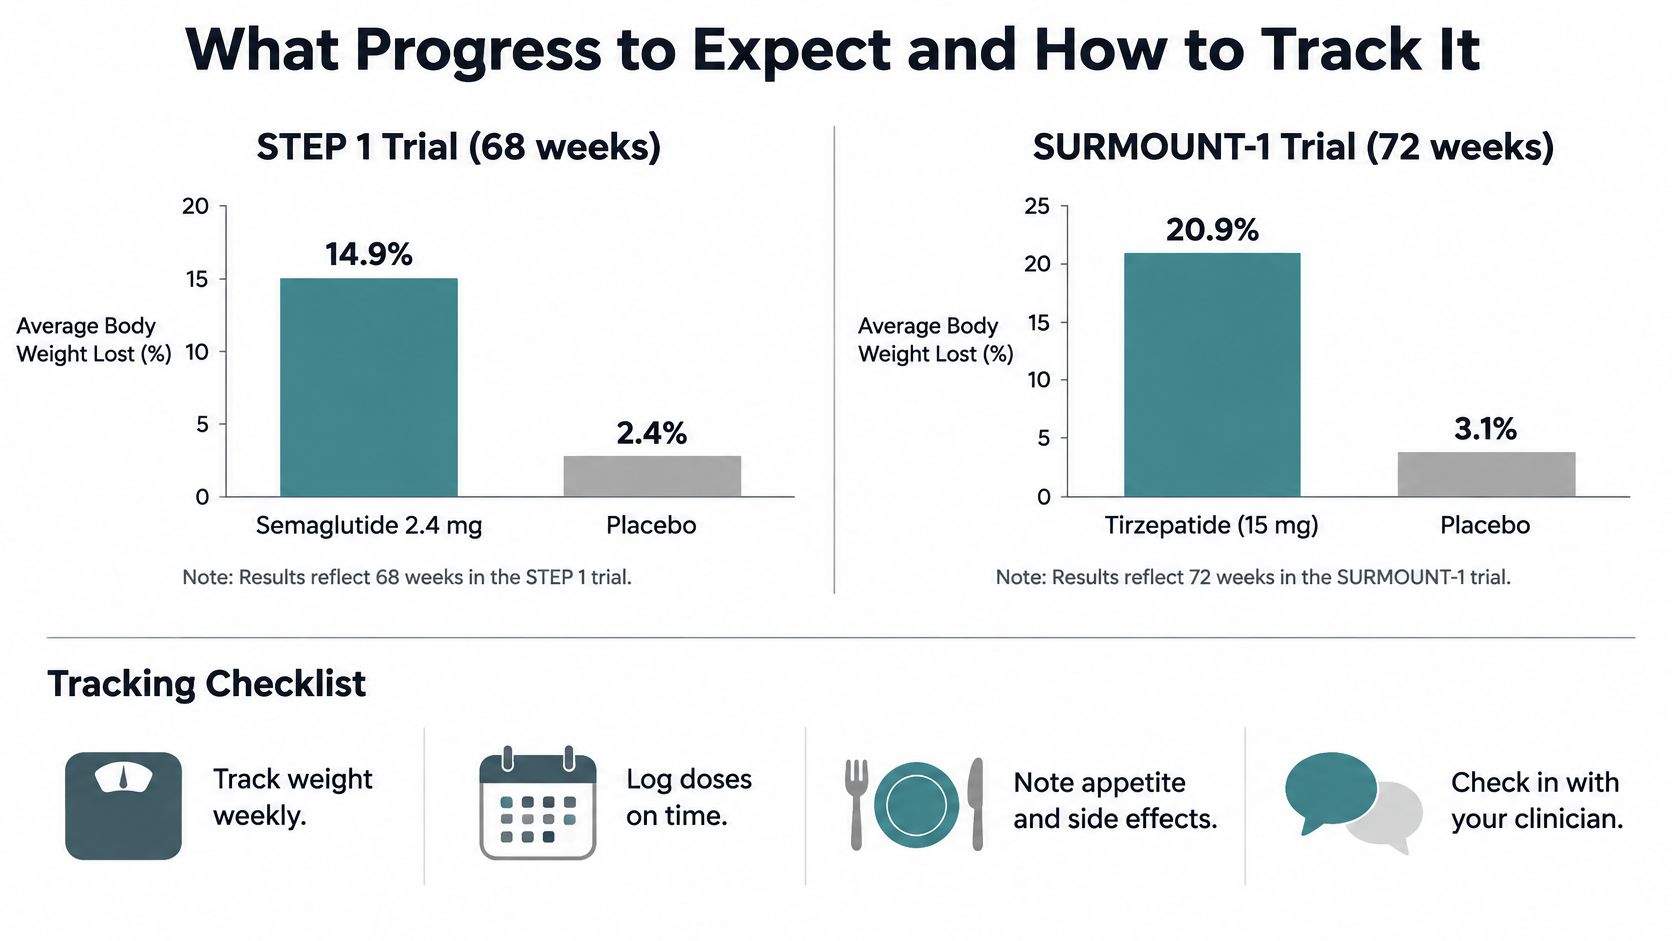
Honest benchmarks come from long trials, not week-four photos. In the 68-week STEP 1 trial of 1,961 adults without diabetes, average body weight fell 14.9% with weekly semaglutide 2.4 mg versus 2.4% with placebo, a difference the New England Journal of Medicine report of STEP 1 found statistically significant. In the 72-week SURMOUNT-1 trial, the American College of Cardiology summary reports mean losses of about 15.0%, 19.5%, and 20.9% at tirzepatide 5, 10, and 15 mg, versus about 3.1% with placebo. Those averages were measured after many months. Your dose, adherence, and tolerability will move the result.
| Timepoint | Benchmark or pattern | What to track |
|---|---|---|
| Weeks 1 to 4 | Dose-start phase; small changes are common | Baseline weight, waist and blood pressure |
| Months 3 to 6 | Steady loss for most participants in trials | Weekly weight averages and waist circumference |
| Week 68 (STEP 1) | Average 14.9% with semaglutide 2.4 mg vs 2.4% with placebo | Trend against the baseline, not daily swings |
| Week 72 (SURMOUNT-1) | Average 15.0%, 19.5% and 20.9% for tirzepatide 5, 10 and 15 mg | Lean-mass signs, energy and nutrition |
| Months 12 and later | Plateaus are common; results vary by person | Maintenance plan and follow-up labs |
Weigh at the same time each week and keep the weekly average. One heavy day after a salty meal doesn't rewrite the month. Measure waist monthly. Note blood pressure and appetite in the same log. A month-by-month view of monthly weight loss expectations for 2026 keeps a slow month from looking like a failed drug. For what those trial averages look like once treatment is underway, see our notes on GLP-1 weight loss results.
When to call and when to wait
Get urgent care for severe abdominal pain that may radiate to the back, persistent vomiting, signs of dehydration, or sudden vision changes. Bring constipation, appetite so low that meals fall apart, dizziness on standing, and fatigue to the next visit. Those are adjustment problems, not emergencies, unless they escalate.
Keep a simple log for the first three months and bring it to every follow-up. The pattern is the data. A single weigh-in isn't.
Stopping, Pausing or Restarting Treatment
Stopping isn't a clean exit. A 2025 real-world study of 7,881 patients, summarized in this PMC report on staying with therapy, found that only 47.0% of semaglutide users and 49.4% of tirzepatide users remained on therapy through the first year. Early discontinuation lined up with much smaller one-year loss, 3.6% versus 11.9% among people who didn't stop. After semaglutide was stopped, withdrawal evidence showed an average regain of 11.6 percentage points, compared with 1.9 points in a placebo arm. Those are averages. Regain isn't identical for everyone, and it isn't a moral failing.

Plan the break before the last pen
Talk with the prescriber before you stop. Ask whether a maintenance dose fits better than a full stop, and how a missed dose should be handled. Write the reason for the break and the date of the last dose in your log. Ask the clinic for a written restart plan so the next clinician isn't guessing.
If you've been off GLP-1 medication for more than three months, we begin two steps below the reported dose. That slower return is about side effects, not about "earning" the old dose back. Confirm the restart dose with the prescriber. The label doesn't set one universal restart rule, so the two-step reduction is the question to ask, not a promise that every clinic uses the same ladder. Our guide on what happens when you stop GLP-1 treatment walks through maintenance versus a full stop in more detail.
Before the next refill, decide with the provider whether the goal is a pause, a maintenance dose, or a full stop. Don't let an empty pen make that decision for you.
Covering the Cost Without Surprises
A prescription that never gets filled isn't treatment. A recent analysis of 9,848 orders from 6,094 patients, covered by the Harvard Gazette report on GLP-1 costs, found that only 60.1% of GLP-1 prescriptions were filled. Average out-of-pocket cost was $71.90 per prescription. Fill rates were lower among Black patients (55.3%) and Hispanic patients (58.4%) than among White patients (60.9%). High out-of-pocket costs, insurance rules, side effects, and shortages all push people off therapy outside trials.
The sticker price is only one line. Prior authorization, formulary changes, pharmacy substitutions, refill timing, and shortages decide whether the medicine arrives. A practical set of questions to ask your insurer beats guessing from a benefits PDF. For a closer look at monthly totals, see our breakdown of GLP-1 weight loss cost.
| Access route | What it usually requires | Check before you start |
|---|---|---|
| Commercial insurance | Prior authorization and a covered product | Whether weight-loss treatment is included and what criteria apply |
| Cash pay | Full monthly price with no coverage | Total monthly cost, refill fees and shipping charges |
| FSA or HSA | Qualifying medical expense documentation | Whether your plan accepts the specific product |
| Medicare or Medicaid | Rules set by the specific state and plan | Whether weight-loss use is covered; confirm with the plan before starting |
| Manufacturer savings programs | Eligibility limits and time limits | Program terms, end dates and whether your plan qualifies |
Checks that prevent a surprise bill
- Written total: Ask the pharmacy for the monthly figure, including fees and shipping.
- Authorization clock: Confirm whether prior authorization is required and how long it takes.
- FSA or HSA: Check that the plan accepts this product, not "weight loss" in general.
- Refill timing: Set a reminder three to five days early.
- Shortage backup: Ask the provider what alternative exists if supply stops.
Nobody can guarantee savings. Compare the written total, not an advertised discount. Write down the monthly amount you can sustain for the next twelve months. If that number only works for month one, the plan isn't ready.
Weight Method connects you with licensed clinicians for GLP-1 evaluation, a prescription when you qualify, and home delivery with follow-up on dosing. If you're ready to see whether semaglutide or tirzepatide fits your history, start with the short quiz and a video visit. Visit Weight Method to check eligibility and talk with a provider.